
Advanced Regenerative Support for Duchenne Muscular Dystrophy (DMD)
Cellular secretome therapy aimed at attenuating chronic myofiber necrosis, calming endomysial inflammation, and stabilizing functional motor capacity.
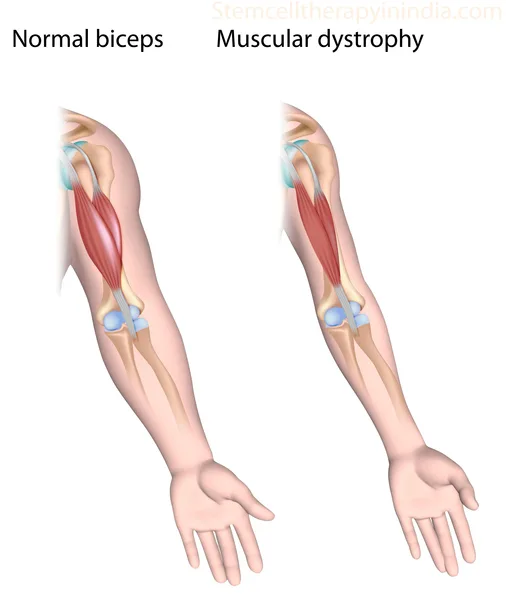 Figure 1: Mesenchymal Stem Cell (MSC) Action Mechanism targeting Myofiber Microenvironment, Satellite Cell Activation & Anti-Fibrotic Protection.
How Stem Cells Target the Mechanism of DMD
Immune Modulation
MSCs modulate chronic inflammatory cascades, reducing cytotoxic M1 macrophage infiltration and inflammatory cytokines.
• Calms hyperactive local inflammation
Anti-Fibrotic Action
Paracrine factors downregulate TGF-β signaling, significantly reducing progressive fibro-fatty connective tissue replacement.
• Preserves muscle elasticity & compliance
Trophic & Stem Support
Bio-trophic secretome factors (HGF, VEGF, IGF-1, BDNF) stimulate resident satellite cells and enhance microvascular perfusion.
• Prolongs motor stamina & function
Therapeutic Rationale
Clinical-grade mesenchymal stem cells (MSCs) deliver potent paracrine immunomodulation and trophic factors directly into the degenerating muscular microenvironment to counter inflammatory breakdown and encourage cellular repair.
Core Objective
Delaying motor decline, preserving upper and lower limb functional capacity, maintaining respiratory muscle vitality (FVC), and enhancing quality of life alongside standard multidisciplinary care.
How Cellular Therapy Targets DMD: 4-Phase Biological Cascade
Evidence-based paracrine signaling, systemic immunomodulation, and microvascular stabilization pathways
M1 to M2 Macrophage Switch
Re-educates hostile pro-inflammatory M1 macrophages into pro-regenerative M2 anti-inflammatory macrophages within the dystrophic muscle microenvironment.
TGF-β Suppression
Secretion of decorin, PGE-2, and hepatocyte growth factor (HGF) suppresses excessive TGF-β signaling, limiting progressive endomysial fibrosis.
Microvascular Perfusion
Upregulation of VEGF and basic fibroblast growth factor (bFGF) restores microcapillary architecture around ischemic and damaged muscle bundles.
Satellite Cell Activation
Bioactive IGF-1 and myokine stimulation activate resident Pax7+ satellite cells to synthesize compensatory structural proteins and support myofiber integrity.
Clinical Perspective: In accordance with ICMR-DBT regulatory framework, cellular therapy for Duchenne Muscular Dystrophy is investigational. Protocols do not correct genetic mutations or produce full-length dystrophin, but aim to slow muscle degradation, maintain functional mobility, and support quality of life alongside standard multidisciplinary care.
Patient Eligibility & Clinical Criteria
Neuromuscular screening criteria evaluating ambulatory status, pulmonary reserve, and cardiac safety
Who May Qualify:
- Confirmed DMD diagnosis via genetic testing (dystrophin gene deletion, duplication, or point mutation) or muscle biopsy.
- Ambulatory boys seeking to prolong independent walking, or non-ambulatory individuals focused on upper-limb strength, posture, and respiratory stability.
- Forced Vital Capacity (FVC) > 50% of predicted value, clinically cleared for international commercial flights.
Mandatory Diagnostic Reports for Pre-Screening:
- • Comprehensive genetic mutation report (MLPA or NGS analysis).
- • Recent Serum Creatine Kinase (CPK / CK) laboratory levels.
- • Recent 2D-Echocardiogram (assessing left ventricular ejection fraction).
- • Spirometry / Pulmonary Function Test (PFT) & short video of motor mobility.
Realistic Potential Benefits & Reported Improvements
Results vary based on the child's age, baseline muscle fibrosis, and functional stage. Therapy is an adjunct to, not an immediate replacement for, routine pediatric neuromuscular care.
Conventional Management vs. Stem Cell Regenerative Strategy
Corticosteroids & Physical Care
- × Does not halt muscle replacement: Progressive fibro-fatty scarring continues over time unchecked.
- × Steroid adverse risks: Long-term weight gain, reduced bone density (osteopenia), and growth delays.
- × Limited regenerative stimulation: Cannot provide bio-trophic growth factors to re-energize exhausted satellite cell niches.
Stem Cell Therapy (Investigational)
- ✓ Downregulates chronic inflammation: Switches destructive M1 macrophages into restorative M2 phenotype.
- ✓ Attenuates endomysial fibrosis: Inhibits TGF-β signaling to preserve muscle compliance and delay contractures.
- ✓ Secretome nourishment: Infuses HGF, VEGF, and IGF-1 to support surviving myofibers and stimulate Pax7+ satellite cells.
Motor Function Preservation
Motor Function Preservation: Slower rate of functional motor decline on standard North Star Ambulatory Assessment (NSAA) scoring.
Upper-Limb Strength & Coordination
Upper-Limb Strength: Sustained dexterity for daily activities, independent feeding, writing, and motorized wheelchair maneuvering.
Respiratory Muscle Stability
Respiratory Muscle Stability: Supportive maintenance of diaphragm and intercostal vitality, reducing recurrent respiratory vulnerabilities.
Serum CPK Stabilization
Serum CPK Stabilization: Downward trend in enzyme leakage, reflecting reduced acute sarcolemmal fragility and membrane rupture.
Overall Stamina & Quality of Life
Overall Stamina & Vitality: Reduced daily exhaustion, enhanced physical endurance, and greater active participation in school and family life.
Why Choose Our Centers in India?
Expert pediatric neuromuscular faculty, certified cGMP cell laboratories, and affordable transparent care
JCI & NABH Infrastructure
JCI & NABH Hospital Infrastructure: Pediatric neuromuscular treatments administered within high-tier tertiary medical centers in Delhi NCR, Mumbai, and Bangalore.
Multidisciplinary Oversight
Multidisciplinary Oversight: Protocols co-managed by senior pediatric neurologists, cellular biologists, physical therapists, and pediatric cardiologists.
Significant Cost Savings
Significant Cost Savings: Complete comprehensive packages starting from $4,000 USD (65%–75% less than clinical trial centers in North America or Western Europe).
Evidence-Guided Candidacy
Evidence-Guided Candidacy: Rigorous pre-screening ensures children are accepted only after a multidisciplinary panel confirms realistic clinical candidacy.
Treatment Costs & Package Inclusions
Transparent international pricing with comprehensive hospital, procedural, and travel inclusions
(comprehensive inpatient package covering targeted intramuscular and systemic cellular therapy based on child's clinical staging).
(Aimed at reducing muscle necrosis, delaying functional decline, and supporting respiratory muscle compliance).
| Country / Region | Typical Package Range | Waiting Period | Clinical Accreditation |
|---|---|---|---|
| India (Our Partner Centers) | Starting from $4,000 USD | 1 – 2 Weeks | JCI / NABH Accredited |
| United States | $28,000 – $50,000 USD | 3 – 6 Months | Clinical Trial Gated |
| Germany & Switzerland | $25,000 – $45,000 USD | 2 – 4 Months | Private Specialty Only |
| Panama / Mexico | $20,000 – $35,000 USD | 2 – 4 Weeks | Variable Regional |
Dedicated International Patient Concierge
Specialized concierge services tailored for international families traveling for pediatric care
Pre-Travel Review
Complimentary Pre-Travel Review: Detailed evaluation of genetic tests, CPK levels, and 2D-echo by our medical board before you book flights.
Medical Visa Support
Medical Visa (e-Med Visa) Assistance: Rapid issuance of official hospital visa invitation letters and priority embassy support for child & parents.
Language Interpreters
Dedicated Language Interpreters: Full-time assistance in English, Arabic, French, Russian, and Spanish throughout the stay.
Private Ground Logistics
Private Ground Logistics: Chauffeur-driven airport pickups, drop-offs, and hospital transfers with wheelchair assistance.
12-Month Structured Follow-Up
12-Month Structured Follow-Up: Scheduled virtual pediatric neuromuscular consults at 1, 3, 6, and 12 months in coordination with your local treating doctor.
Logistics & Accessible Accommodation
Accessible recovery suites with specialized pediatric nutrition and seamless hospital transfers
Curated Accommodations
Curated Accommodations: Partner bookings at 4-star and 5-star serviced apartments and hotels located within 10–15 minutes of the medical center with step-free access and elevators.
Family Amenities
Family-Friendly Amenities: Spacious inpatient rooms and private suites fully equipped to accommodate traveling parents, siblings, and dedicated attendants.
Personalized Services
Personalized Patient Services: Assistance with customized family meals (Halal, Vegetarian, Continental), local SIM cards, currency exchange, and 24/7 guest relations.
Typical Treatment Schedule (4–7 Days in India)
Comprehensive inpatient schedule from baseline pediatric workup to fit-to-fly clearance
 Figure 2: Clinical Treatment Pathway — Diagnostic Pre-Screening, cGMP Cell Processing, Targeted Administration & Post-Infusion Care.
Day 1: Arrival & Baseline Neuromuscular Workup
Airport reception, hospital check-in, pediatric neurology consultation, baseline CPK blood testing, echocardiogram check, and physical therapy evaluation.
Day 2: Targeted Cellular Administration
Administration of clinical-grade certified UC-MSCs via combined multimodal systemic IV infusion and targeted intramuscular micro-infusion under sterile operating suites.
Day 3: Adjunctive Neurotrophic & Physical Therapy
Supportive antioxidant/metabolic infusion and specialized pediatric physical therapy session focusing on passive stretching and motor neuron facilitation.
Day 4: Clinical Monitoring & Biomarker Review
Evaluation of clinical vital stability, post-procedure pediatric check, and tailored home exercise regimen guidance for parents.
Day 5–7: Discharge Summary & Departure
Final physician consultation, issuance of comprehensive discharge documentation, remote follow-up schedule, and airport transfer with fit-to-fly clearance.
Procedural Safety & Risk Disclosures
Per medical guidelines, patients and parents must understand procedural considerations and safety guardrails:
Critical Safety Rule
Critical Safety Rule: Stem cell therapy is an investigational supportive treatment and does not replace prescribed corticosteroids (Deflazacort/Prednisone) or cardiac medications. Patients must continue all routine therapies under the supervision of their pediatric neurologist.
Procedural Side Effects
Procedural Side Effects: Mild, self-limiting transient reactions such as low-grade fever (< 38°C), temporary fatigue, or localized soreness at the injection site resolving within 24–48 hours.
Quality Assurance
Quality Assurance: All cell batches undergo rigorous testing for viability (>85%), endotoxins, sterility, mycoplasma, and normal karyotyping prior to clinical administration.
Frequently Asked Questions: DMD Care
Evidence-based clinical guidance regarding cellular therapy protocols, motor outcomes, and international travel
No, stem cell therapy is not recognized as a definitive or permanent cure. Under Indian Council of Medical Research (ICMR) and CDSCO clinical guidelines, cellular therapy for Duchenne Muscular Dystrophy (DMD) is an investigational and supportive treatment. Its objective is to modulate pathogenic immune activity, release neurotrophic and cytoprotective paracrine factors, and slow down progression to improve quality of life under strict institutional ethics oversight.
Umbilical cord-derived Mesenchymal Stem Cells (UC-MSCs) act primarily through paracrine immunomodulation and secretome release. They downregulate pro-inflammatory cytokines, modulate hyperactive cytotoxic T-cells, inhibit excessive fibrotic scarring, and secrete restorative growth factors (such as HGF, VEGF, BDNF, and IL-10) that support microvascular circulation and cellular tissue survival.
The comprehensive outpatient daycare protocol requires approximately 4 to 7 Days in India. Day 1 involves baseline diagnostic blood panels, imaging, and specialty evaluation by a Pediatric Neurology & Neuromuscular Medicine board. Days 2 and 3 include monitored cellular infusion (Multimodal Systemic IV & Targeted Intramuscular Administration) under vital telemetry, followed by post-procedure observation, mobility guidance, and fit-to-fly clearance on Day 7.
Certified cGMP-processed allogeneic UC-MSCs possess an established safety profile with zero risk of donor graft-versus-host disease (GvHD). Common transient reactions include self-limiting low-grade fever (< 38°C / 100.4°F), temporary fatigue, or mild injection-site soreness resolving within 24–48 hours. Patients undergo pre-infusion safety checks and continuous bedside monitoring.
Comprehensive international treatment packages start from $4,000 USD. This transparent pricing includes clinical-grade certified UC-MSC biologicals (flow-cytometry verified >85% viability), specialized hospital procedural suites, doctor consultations, routine baseline safety labs, medical visa (MED) invitation support, and 12 months of structured remote follow-up.
Before confirming medical travel, international patients must submit recent clinical diagnostic reports (genetic MLPA/NGS reports, serum CPK levels, 2D-echo, and spirometry records) for preliminary evaluation by our medical board. Our clinical team reviews the records within 24 to 48 hours to confirm candidacy before issuing official visa invitation letters.
Peer-Reviewed Scientific Citations & Clinical References
Key published clinical trials and peer-reviewed literature supporting cellular therapy in Duchenne Muscular Dystrophy:
Mandatory Regulatory & Legal Disclaimer
Important Medical Notice:
Stem cell therapy for Duchenne Muscular Dystrophy (DMD) is an investigational regenerative approach focused on immune modulation and cellular preservation; it does not constitute an absolute genetic cure, nor does it generate full-length dystrophin protein directly. Long-term outcomes vary according to patient age, baseline muscle fibrosis, and functional staging. In India, cell processing and therapeutic protocols follow ethical frameworks and guidelines overseen by institutional ethics committees (IEC/IC-SCR) and national regulatory bodies (ICMR/CDSCO). Patients should never alter or discontinue their daily medications (such as corticosteroids or cardioprotective therapies) without direct authorization and supervision from their managing pediatric neurologist.