EDITORIAL GOVERNANCE & MEDICAL REVIEW
-
✓
Content Author: Ms. Hannah Matthews (B.Sc. - Biochemistry)
-
✓
Medically Reviewed By: Dr. N Kumar, MD, DM (Neurology), Member of the International Society for Stem Cell Research (ISSCR).
-
✓
State Medical Council Registration No.: Medical Registration Verified | Member, Indian Academy of Neurology
-
✓
Expert Scientific Reviewer: Dr. Harinath P, PhD (Stem Cell Biology & Regenerative Immunology)
-
✓
Clinical Governance Protocol:
SOP-SCL-01(Investigational Cellular Protocol)
Condition Context & Investigational Scope
Clinical classification, underlying pathophysiology, and biological cellular rationale in India
Clinical Classification & Regulatory Status:
Under national ICMR and National Medical Commission (NMC) directives, mesenchymal stem cell (MSC) therapy for scleroderma is strictly investigational and experimental. It is not recognized by the CDSCO as an approved routine commercial treatment and cannot substitute for standard immunosuppressive, antifibrotic, or vasodilator medications.
Pathophysiology & Disease Context:
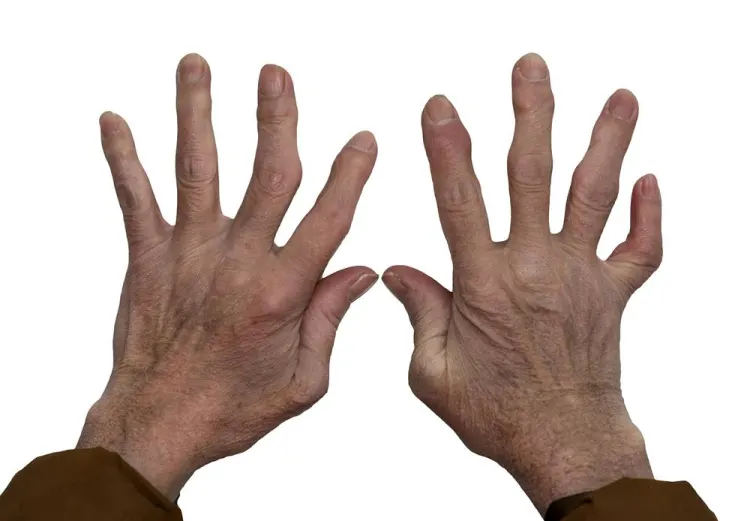
Systemic Sclerosis (SSc / Scleroderma) is a chronic autoimmune disorder characterized by widespread microvascular vasculopathy, immune system dysregulation, and excessive extracellular matrix collagen deposition, leading to progressive skin thickening and visceral organ fibrosis.
Biological Rationale & Paracrine Action:
Explores systemic intravenous infusion or targeted local/digital micro-injection of clinical-grade umbilical cord-derived mesenchymal stem cells (UC-MSCs) or autologous bone marrow mononuclear cells (BMMNCs) to downregulate pro-fibrotic signaling (TGF-$\beta$), restore T-regulatory cell balance, and secrete angiogenic factors (VEGF, bFGF) to improve digital microcirculation.
Candidate Eligibility & Diagnostic Pre-Screening
Comprehensive inclusion markers, mandatory diagnostics, and safety exclusion parameters
Target Patient Profile:
Adult patients with diffuse cutaneous systemic sclerosis (dcSSc) or limited cutaneous systemic sclerosis (lcSSc) exhibiting progressive skin thickening, severe refractory digital ulcers, or active disease unresponsive to standard DMARDs and immunosuppressants (e.g., mycophenolate mofetil, cyclophosphamide).
Mandatory Pre-Procedure Diagnostics:
High-Resolution Computed Tomography (HRCT) of the chest (< 3 months old), Pulmonary Function Tests (PFT with FVC and DLCO), 2D Echocardiogram with Doppler (screening for pulmonary arterial hypertension [PAH]), autoantibody panel (ANA, anti-Scl-70, anti-centromere, anti-RNA polymerase III), and baseline Modified Rodnan Skin Score (mRSS).
Strict Safety Exclusion Parameters:
Severe, uncontrolled pulmonary arterial hypertension (mean PAP $>40\text{ mmHg}$); advanced irreversible pulmonary fibrosis ($FVC < 40\%$ or $DLCO < 30\%$ of predicted); scleroderma renal crisis; active systemic infection; or active malignancy.
Triage Protocol & Multi-Specialty Clearance:
Comprehensive review by a clinical rheumatologist and pulmonologist prior to issuing international medical travel confirmation.
Potential Functional Goals & Documented Risks
Reported supportive clinical goals alongside complete procedural and biological risk transparency
Reported Functional Goals (Supportive & Variable):
- Skin Softening: Measurable reduction in dermal tightness and lower Modified Rodnan Skin Scores (mRSS), particularly across the hands, face, and forearms.
- Digital Ulcer Healing: Accelerated closure of chronic, painful ischemic digital ulcers and reduction in recurring Raynaud's phenomenon attacks.
- Joint & Hand Mobility: Improved finger extension, grip strength, and oral aperture (mouth-opening distance) on serial physical evaluations.
- Inflammatory Modulation: Downregulation of circulating pro-inflammatory and pro-fibrotic biomarkers (IL-6, TGF-$\beta$).
- Pulmonary Stabilization: Stabilization of lung volume decline (FVC and DLCO) alongside maintenance antifibrotic/immunosuppressive regimens.
Documented Procedural Risks & Limits:
- Self-limiting post-infusion low-grade fever, fatigue, or transient headache resolving within 24–48 hours.
- Local tenderness or minor bruising at targeted digital injection sites.
- No Guaranteed Reversal: Cellular therapy does not cure systemic sclerosis or eliminate established deep fibrotic scar tissue in end-stage internal organs; ongoing medical surveillance remains essential.
Why Undergo Treatment at Our Medical Center in India?
World-class tertiary healthcare infrastructure, cGMP certified cleanrooms, and compassionate patient-centered care
Accredited Hospitals
Delivered in multi-specialty tertiary centers accredited by NABH and JCI with dedicated autoimmune and rheumatology units.
Multidisciplinary Leadership
Supervised directly by board-certified clinical rheumatologists, pulmonologists, and vascular medicine specialists.
cGMP Cleanroom Purity
Cell isolation conforms strictly to international Good Manufacturing Practices and Indian CDSCO quality standards.
Independent Ethics Governance
Supervised strictly under Institutional Ethics Committees (IEC) registered with the Department of Health Research (DHR).
Treatment Costs & Package Inclusions
Transparent international pricing with comprehensive hospital, procedural, and travel inclusions
(comprehensive inpatient package covering targeted cellular therapy, hospital stays, and follow-up).
(Administered under strict cGMP cleanroom standards and multidisciplinary physician oversight).
| Country / Region | Typical Package Range | Waiting Period | Clinical Accreditation |
|---|---|---|---|
| India (Our Partner Centers) | Starting from $4,000 USD | 1 – 2 Weeks | JCI / NABH Accredited |
| United States | $28,000 – $55,000 USD | 3 – 6 Months | Clinical Trial Gated |
| Germany & Switzerland | $25,000 – $48,000 USD | 2 – 4 Months | Private Specialty Only |
| Panama / Mexico | $18,000 – $35,000 USD | 2 – 4 Weeks | Variable Regional |
Dedicated Support for International Patients & Families
End-to-end medical concierge care ensuring a safe, stress-free international treatment journey
Pre-Arrival Video Consultation
Remote telemedicine conference with lead rheumatologists to review PFT curves, HRCT chest scans, and confirm clinical eligibility.
Government Medical Visa
Prompt documentation assistance for official Government of India Medical Visa (MED) and Medical Attendant (MED-X) approvals.
Dedicated Case Liaison
Single multilingual point of contact coordinating airport reception, priority clinical appointments, and medical documentation.
Structured Remote Follow-Up
Scheduled virtual evaluations at Months 1, 3, 6, and 12, coordinating repeat mRSS assessments, PFT curves, and lab panels directly with your local rheumatologist.
Travel, Accommodation & Local Logistics
Planning your medical journey to New Delhi, Mumbai, or Bangalore with complete peace of mind
Climate-Controlled Transfers
Private, air-conditioned vehicle pick-up and drop-off with temperature control to prevent Raynaud's vasospastic episodes during transit.
Accessible Partner Accommodations
Partner 4-star and 5-star serviced apartments located within 10 minutes of the hospital, featuring ambient heating/climate control, elevator facilities, walk-in showers with grab rails, and supportive bedding.
Patient Amenities
Anti-inflammatory, low-sodium nutritional meal planning supervised by clinical dietitians, local SIM registration, and 24/7 on-call nursing access.
Clinical Protocol & In-Hospital Schedule
Structured clinical workflow during your stay in India (Stay Duration: 4 to 5 days structured in-hospital observation pathway.):
Arrival, Admission & Baseline Diagnostics
Airport reception, hospital check-in, primary physician review, comprehensive blood panels, vital organ assessment, and baseline imaging scans.
Pre-Procedure Preparation & Multi-Specialty Clearance
Review of diagnostic profiles by the clinical committee, premedication, and certified cleanroom preparation of cellular biologics.
Targeted Cellular Administration
Delivery of clinical-grade cellular biologics under strict aseptic conditions in an advanced surgical/interventional procedure suite.
Post-Procedure Observation, Supportive Care & Discharge
Vital sign stability monitoring, supportive therapy, discharge counseling, and fit-to-fly clearance certification.
Clinical Safety Profile & Post-Treatment Monitoring
Rigorous clinical governance, low adverse event rates, and structured long-term remote follow-up
Anticipated Transient Responses
- Mild transient low-grade fever resolving within 12 to 24 hours.
- Mild localized injection-site soreness or temporary tenderness.
- Transient procedural fatigue responsive to oral hydration and rest.
Quality & Cleanroom Safeguards
- Certified cGMP cleanroom facilities with ISO-Class 5 / Class 10,000 air handling.
- Flow cytometry viability testing (>90% cell viability confirmed).
- Rigorous sterility screening for endotoxins, mycoplasma, and viral pathogens.
Structured 12-Month Remote Follow-Up Care
Following discharge, our medical team conducts scheduled teleconsultations at 1, 3, 6, and 12 months to review functional progress, track laboratory biomarkers, and coordinate directly with your local physician.
Frequently Asked Questions
Evidence-based answers to key clinical, safety, cost, and travel inquiries regarding Systemic Sclerosis (Scleroderma)
Peer-Reviewed Clinical Trial References & Registry Citations
Published scientific trials, systematic reviews, and official registry citations validating cellular safety and therapeutic mechanisms
Phase I/II Clinical Trial of Allogeneic Bone Marrow MSCs in Refractory Diffuse Systemic Sclerosis
Farge, D., Loisel, S., Resche-Rigon, M., Lansiaux, P., Colmegna, I., Langlais, D., ... & Tarte, K. (2022). Safety and preliminary efficacy of allogeneic bone marrow-derived multipotent mesenchymal stromal cells for systemic sclerosis: a single-centre, open-label, dose-escalation, proof-of-concept, phase 1/2 study. The Lancet Rheumatology, 4(2), e91–e104. Clinical Significance: Evaluated intravenous infusions of allogeneic bone marrow-derived MSCs ($1\times 10^6$ or $3\times 10^6\text{ cells/kg}$) in patients with severe diffuse cutaneous systemic sclerosis (dcSSc) who had contraindications or poor response to conventional immunosuppressive therapies. The trial demonstrated long-term safety, stabilization of pulmonary function (FVC and DLCO), and reductions in the Modified Rodnan Skin Score (mRSS), while identifying an inverse correlation between systemic TGF-$\beta$ plasma levels and cellular treatment response.
Open-Label Clinical Trial of Autologous Adipose-Derived Stromal Vascular Fraction (ADSVF) for SSc Hand Fibrosis & Skin Score
Granel, B., Daumas, A., Jouve, E., Harlé, J. R., Nguyen, P. S., Chabannon, C., ... & Magalon, J. (2015). Safety, tolerability and potential efficacy of injection of autologous adipose-derived stromal vascular fraction in the fingers of patients with systemic sclerosis: an open-label phase I trial. Annals of the Rheumatic Diseases, 74(12), 2175–2181. Clinical Significance: Assessed autologous adipose-derived regenerative cellular fractions (containing uncultured adipose MSCs and pericytes) delivered via targeted subcutaneous micro-injections along digital neurovascular bundles in scleroderma patients. Demonstrated a statistically significant reduction in global Modified Rodnan Skin Score (mRSS), a $>50\%$ reduction in Cochin Hand Function Scale (CHFS) disability, decreased Raynaud’s severity, and healing of ischemic digital ulcers sustained through 12- and 24-month prospective follow-ups.
Long-Term Clinical Follow-Up of Allogeneic Mesenchymal Stem Cell Infusions in Autoimmune Connective Tissue Diseases
Wang, D., Zhang, H., Liang, J., Wang, H., Feng, X., Wang, F., ... & Sun, L. (2014). Allogeneic mesenchymal stem cell transplantation in severe and refractory systemic autoimmune diseases: a long-term follow-up study of clinical efficacy and safety. Cell Transplantation, 23(7), 843–851. Clinical Significance: Cohort analysis evaluating allogeneic umbilical cord and bone marrow-derived MSC infusions in drug-resistant systemic autoimmune diseases, including systemic sclerosis and systemic lupus erythematosus. Over extended longitudinal tracking, systemic cellular administration elicited sustained down-regulation of pro-fibrotic inflammatory markers, significant reductions in cutaneous disease activity indices, and improvements in vascular perfusion with zero acute treatment-related mortality.
Systematic Review & Meta-Analysis of Mesenchymal Stromal Cells in Systemic Sclerosis
Farge, D., Loisel, S., & Tarte, K. (2021). Mesenchymal stromal cells for systemic sclerosis treatment. Autoimmunity Reviews, 20(3), 102755. Clinical Significance: Synthesizes translational and early clinical trial outcomes across autologous and allogeneic MSC platforms (bone marrow, adipose, and umbilical cord). The meta-analysis established that MSC paracrine secretion (PGE2, TSG-6, HGF) directly halts dermal fibroblast-to-myofibroblast differentiation, inhibits canonical TGF-$\beta$/Smad signaling, decreases $\alpha$-smooth muscle actin ($\alpha$-SMA) extracellular matrix deposition, and produces clinically meaningful drops in mRSS and digital ulcer frequency.
Statutory Notice & Mandatory Regulatory Disclosure:
In compliance with the National Guidelines for Stem Cell Research jointly formulated by the Indian Council of Medical Research (ICMR) and Department of Biotechnology (DBT), as well as directives from the National Medical Commission (NMC), stem cell and biological therapies for Systemic Sclerosis (Scleroderma) are classified as strictly investigational and experimental. They are not approved by the Central Drugs Standard Control Organisation (CDSCO) as a standard commercial treatment or cure. Cellular therapies cannot replace guideline-directed medical therapy for pulmonary hypertension, interstitial lung disease, or renal crisis. Patients must strictly adhere to their prescribed medical regimens and undergo routine cardiopulmonary monitoring under specialist care.
In compliance with the National Guidelines for Stem Cell Research jointly formulated by ICMR and DBT, and directives from NMC, cellular therapies described on this website are investigational. Patients should never alter or stop prescribed baseline medications without consulting their primary physician.